Confirmation
Download PDF
Open All
PR16: Zoll ECG Acquisition
Applicable To
Introduction
The 12-lead electrocardiogram is one of the most useful diagnostic tests in medicine and is a critical component in out-of-hospital care and decision-making. It allows paramedics to view the rhythm of the heart and provides important information about the state of blood flow to various regions of the heart.
Other than a STEMI flag, observing abnormal ECG findings should not be the basis for altering decision making. A normal ECG should not change decision making (treatment, transport, layered response, or conveyance decisions). Life threatening pathologies may have a normal ECG.
Paramedics are to use clinical judgement to determine if 12 lead ECG should be acquired on scene or enroute. 12 lead ECG acquisition does not take priority over critical interventions.
Indications
Limb Leads Indications
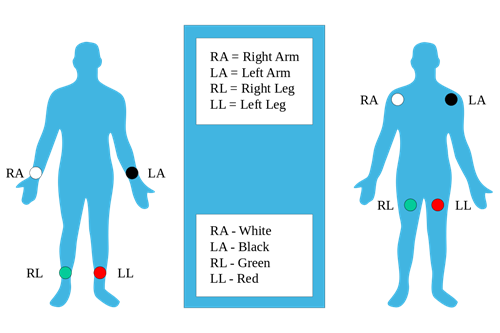
imb leads use four electrodes to continuously monitor the hearts rhythm, the limb leads must be placed prior to acquiring a 12 lead.
Indications for applying the limb leads are:
-
- In preparation to acquire a 12-lead ECG in patients with signs or symptoms suggestive of cardiac ischemia, arrhythmia, or acute myocardial infarction.
- Monitoring and documenting cardiac rhythm abnormalities, such as bradycardia, tachycardia, or irregular rhythms that can be communicated to receiving hospital staff.
- At the request of the sending Physician and Patient Transport Coordination Centre (PTCC) for interfacility transfer
12-Lead Indications
-
Suspicion of cardiac ischemia or rhythm disturbance.
NOTE: Indications for an ECG can vary: common presentations include chest pain, "heaviness", or discomfort associated with shortness of breath, nausea, and/or diaphoresis.
Be aware that although these are common findings, certain populations – in particular, women, the elderly, those with a history of diabetes, and younger individuals – may present with weakness or fatigue, syncope/presyncope, dizziness abdominal pain, upper back pain and nausea.
Contraindications
- As a diagnostic procedure, there are few absolute contraindications to ECG acquisition; paramedics must ensure that the time needed to acquire a 12-lead ECG does not interfere with priority patient management tasks
Procedure
Procedure: Limb Leads
- Obtain verbal consent
- Perform approved skin prep technique - see notes below
- Place limb leads in approved location
- Arms: RA and LA - right and left deltoids, wrists as alternatives
- Legs: RL and LL - LL on left lower leg, RL on either right or left lower leg
Procedure: Standard 12-Lead ECG
- Obtain verbal consent
- Perform approved skin prep technique - see notes below
- Place limb leads in approved location
- Arms: RA and LA - right and left deltoids
- Legs: RL and LL - LL on left lower leg, RL on either right or left lower leg
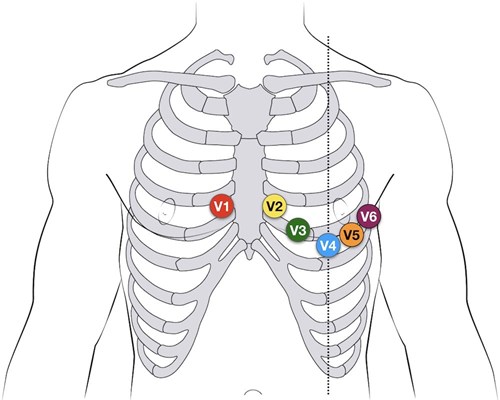
- Landmark and place precoridal leads in their appropriate locations as indicated
- Enter patient demographics **NOTE** Demographics must be entered prior to acquisition otherwise they will not be transmitted on the ECG to EPOS or pPCI. Please enter this information accurately - aim to enter PHN on all ECGs.
- Obtain 12-lead ECG. Ask patient to remain still.
- For PCP
-
- If 12 lead ECG flags STEMI or acute MI, follow PR58:PCP STEMI Clinical Pathway.
- If the 12 Lead flags STEMI follow local STEMI clincial pathway if one exists.
- If 12 Lead flags ACUTE MI contact clinicall for support and consider repeat 12 Lead ECGs. .

-
- For ACP
- Follow established process for managing pre-hospital STEMI
**NOTE: IF DEMOGRAPHICS ARE NOT ENTerED PRIOR TO ECG ACQUISITION, THEY WILL NOT BE TRANSMITTED ON THAT ECG**
Limb Lead Placement
Precordial Lead Placement
- V1 is located at the fourth intercostal space, on the right of the sternum.
- V2 is also at the fourth intercostal space, to the left of the sternum.
- V3 is located between V2 and V4. For ease of placement, inexperienced operators should place V3 after V4 has been placed.
- V4 is placed at the fifth intercostal space on the mid-clavicular line. Generally, this will be inferior to the left nipple.
- V5 is placed at the fifth intercostal space, on the anterior axillary line.
- V6 is level with V5 on the mid-axillary line.


Procedure: Posterior Leads (ACP only)
In some cases, a view of the posterior heart is needed, particularly in patients with marked precordial ST depression.
- Acquire a standard 12-lead ECG.
- Disconnect V4, V5, and V6 from their traditional placements.
- Using new electrodes, with the patient leaning forward:

- Place the V4 electrode on the left posterior axillary line in the same plane as V6. This electrode becomes V7.
- Place the V5 electrode at the tip of the left scapula, in the same horizontal plane as V6. This electrode becomes V8.
- Place the V6 in the left paraspinal region, in the same plane as the other electrodes. This electrode becomes V9.
- Acquire the ECG.
- Once the LifePak 15 prints the ECG, mark V4, V5, and V6 with their new designations of V7, V8, and V9 on the rhythm strip.
Procedure: Right-Sided Leads (ACP only)
The right-sided chest lead is very helpful in diagnosing right ventricular infarctions.
- Acquire a standard 12-lead ECG.
- Disconnect V4 from its traditional placement.
- Using a new electrode, place V4 at the fifth intercostal space on the mid-clavicular line. This becomes V4R and is essentially the “mirror image” of V4 on the left chest.

- Acquire the ECG.
- Once the ECG is printed, mark V4 as V4R on the rhythm strip.
Procedure: Lewis Lead (ACP only)
The Lewis Lead ECG is used in order to have a specific and detailed view of atrial activity. This may be clinically useful when atrial flutter is suspected but not clearly demonstrated, or to detect P waves in a wide complex tachycardia.
- To create the Lewis Lead, move the right arm electrode to the 2nd intercostal space, right of the sternum. Move the left arm electrode to the 4th intercostal space, right of the sternum (traditionally the landmark for V1).
- Leave the lower limb leads in place.
- To read the Lewis Lead, print rhythm strip in 'Lead I'.

Notes
- ECG acquisition is a relatively intimate procedure. Paramedics should strive to preserve patient dignity whenever possible by using gowns or towels.
- Tips for improved ECG quality:
- Skin preparation can significantly improve the quality of the ECG signal. Shave hair at the site of electrode placement whenever possible. An alcohol wipe can be used to help dry the skin when it is sweaty and a gauze pad can be used to rub the skin briskly to remove sweat, oil, and dead skin cells, improving contact.
- The conduction of ECG electrodes is improved as they warm. Consider ensuring that electrodes are stored at room temperature (up to body temperature is ideal).
- Do not press on the center of the electrode while applying it to the patient. Press around the circumference of the electrode to ensure proper adhesion.
- Patients should be supine or semi-recumbent during ECG acquisition. Their limbs should be fully supported.
- The Angle of Louis can be identified by placing a finger in the notch at the top of the sternum. Move the finger downward until a slight ridge or bump is felt, then slide the finger laterally to the patient’s right side to locate the second rib and the second intercostal space immediately below. Count down two more intercostal spaces; this is the fourth intercostal space and V1 is placed immediately adjacent to the sternum.
- V4 may be placed under the breast if necessary.
- In patients who have been resuscitated from cardiac arrest, wait at least ten minutes following sustained return of spontaneous circulation before attempting to record a 12-lead ECG.